SAMe for osteoarthritis: older comparative trials do not settle modern use
SAMe studies report inconsistent osteoarthritis results. Trial design, comparator choice, onset and interaction risks all shape the answer.
SAMe has shown mixed results in older, often small trials, leaving effectiveness, optimal use and long-term safety insufficiently settled.
A molecule made in the body is still a supplement intervention
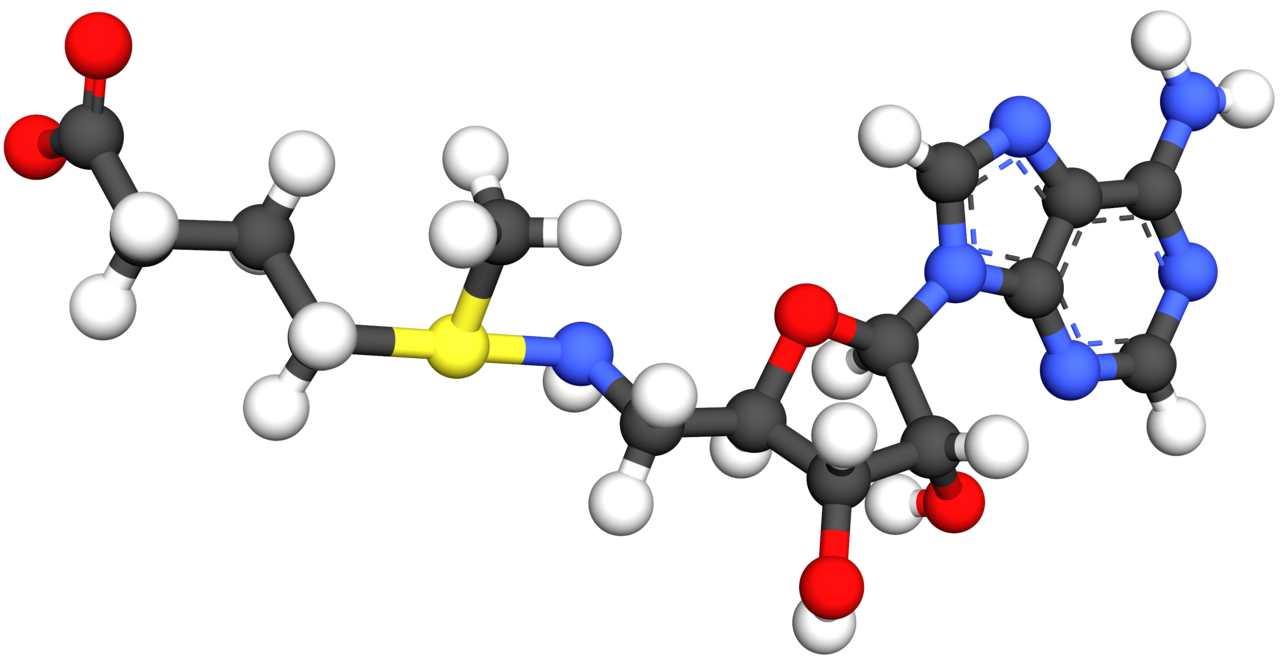
S-adenosyl-L-methionine, commonly called SAMe, participates in normal biochemical reactions and is also sold as a dietary supplement. Marketing sometimes treats that natural presence as evidence that taking more will relieve osteoarthritis. Endogenous function does not answer the clinical question. Randomized trials must still show that a specific oral product improves a relevant outcome with acceptable risk.
NCCIH describes osteoarthritis studies of SAMe as inconsistent. Some comparisons suggested symptom relief similar to nonsteroidal anti-inflammatory medicines, while placebo-controlled studies were less persuasive. That pattern makes trial design especially important: an active-comparator result does not automatically prove that either treatment beat placebo under the same conditions.

The celecoxib comparison was small and time-dependent
A double-blind crossover trial enrolled 61 adults with knee osteoarthritis and compared SAMe with celecoxib. Celecoxib reduced pain more during the first month; by the second month the groups did not differ significantly on many measures. The authors proposed that SAMe had a slower onset. Fifty-six participants completed the study, so the evidence came from a small sample and a design in which treatment periods can influence one another.
“As effective as” language requires caution. Failure to detect a difference is not always proof of equivalence, especially in a small trial not designed with a formal noninferiority margin. The result is better read as an exploratory comparison that generated a hypothesis about timing, not a license to substitute SAMe for prescribed care.
Placebo-controlled evidence remained inconclusive
A Cochrane review identified four placebo-controlled trials with 656 participants. The pooled estimate for pain was small and crossed the line of no effect, while the function estimate was imprecise and inconsistent. Reporting and methodologic quality were poor, and serious adverse events were not reported in a way that allowed a dependable conclusion.
An earlier meta-analysis reached a more favorable view when combining comparisons with placebo and anti-inflammatory medicines. The contrast between reviews shows why readers should inspect included studies, comparators and quality assessments. An older body of research does not become stronger merely because several abstracts can be counted.
Product quality and interactions belong in the decision
SAMe products may differ in stability, formulation and labeled amount. A trial result cannot be assumed to transfer to a product that does not reliably deliver the studied compound. Independent quality testing can address identity and contamination, but it does not prove effectiveness. Quality certification and clinical evidence answer different questions.
SAMe can interact with medicines and may be inappropriate in some psychiatric or neurologic contexts. Because it affects pathways related to serotonin, combining it with antidepressants or other serotonergic agents deserves professional review. Mild adverse effects in a short osteoarthritis trial do not establish safety for every person, dose or duration.
Do not let an uncertain supplement displace proven care
Osteoarthritis management can include exercise, physical therapy, weight management when relevant, medicines and procedures selected for the individual. SAMe has not been shown to regenerate cartilage or halt structural progression. A person with a new swollen joint, injury, rapidly changing symptoms or systemic illness needs assessment rather than a supplement experiment.
The evidence-based description is restrained: SAMe may have symptom effects for some people, but the placebo-controlled evidence and long-term safety base are not strong enough for confident general recommendations. If it is considered, the exact product, medicines, mental-health history, goals and a stop rule for lack of benefit should be discussed with a qualified clinician.
The age of much of the evidence creates another limitation. Manufacturing, diagnostic criteria and background osteoarthritis care have changed, while many older studies provide less complete reporting than current standards expect. Modern registration, prespecified outcomes and full adverse-event reporting would make a new trial easier to interpret. Independent replication would matter as well. Until such evidence exists, confident dose comparisons or product rankings are not justified by the available literature.
Sources & further reading
This article provides educational information. Ask a qualified clinician or pharmacist about your symptoms, medical conditions, medicines and supplement interactions.