
CBD for osteoarthritis pain: three randomized trials found no meaningful advantage
Recent randomized trials of oral CBD for knee and hand osteoarthritis did not beat placebo, and one high-dose study found more adverse events.
Randomized trials do not currently support oral CBD for osteoarthritis pain, while liver, interaction and product-quality risks remain relevant.
Consumer popularity moved ahead of clinical evidence
CBD products are widely marketed for pain, sleep and inflammation, often with testimonials rather than condition-specific trials. Preclinical findings can show that cannabinoids affect signaling pathways, but they cannot establish pain relief in people with osteoarthritis. Randomized placebo-controlled research is especially important because pain varies and expectations can produce substantial improvement in both groups.
FDA states that CBD cannot lawfully be marketed as a dietary supplement under current federal law and warns about unapproved therapeutic claims, liver injury, drug interactions and uncertain product quality. A retail label is not evidence of FDA review for arthritis.

High-dose CBD did not add pain relief
A randomized double-blind trial enrolled 86 people with painful chronic knee osteoarthritis receiving three grams of acetaminophen daily. Participants added either 600 milligrams of oral CBD or placebo for eight weeks. WOMAC pain fell by nearly the same amount in both groups, with no significant between-group difference.
Adverse events were more frequent with CBD, and liver-enzyme elevations occurred more often in the CBD group. The trial had substantial dropout, but its intention-to-treat result does not support high-dose CBD as an analgesic add-on in this setting. More exposure did not translate into more benefit.
Hand arthritis and a newer oil trial were also negative
A 12-week randomized trial of synthetic CBD in 136 people with hand osteoarthritis or psoriatic arthritis found no clinically or statistically significant pain advantage over placebo. Sleep, anxiety, depression and disability outcomes also did not differ, challenging the idea that CBD would improve pain indirectly through those domains.
A CBD-rich cannabis-oil trial published in late 2025 followed people with knee osteoarthritis for 60 days. Both groups improved, but pain and secondary outcomes did not differ significantly. The oil was tolerated in that study, yet a negative efficacy result cannot be turned into a recommendation based on tolerability alone.
Different formulations do not justify unlimited benefit claims
The trials used different CBD amounts and preparations, so none proves that every possible cannabinoid formulation is ineffective. That uncertainty cuts both ways. A seller cannot claim that an untested topical, gummy or full-spectrum oil works simply because another product used a different dose.
CBD can affect drug metabolism, sedation and liver function. Products may contain inaccurate amounts or unexpected THC and contaminants. People taking medicines, using alcohol or sedatives, driving, or managing liver disease need a professional safety review rather than dosing advice from marketing copy.
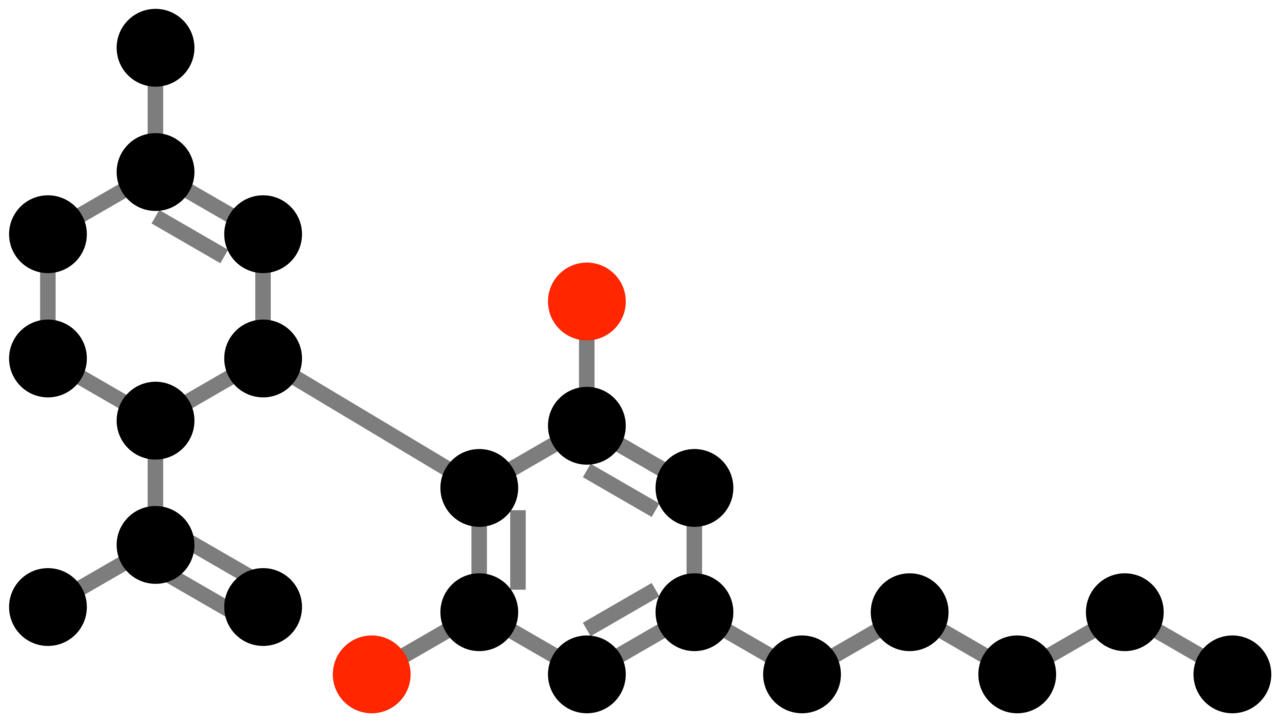
The current answer is clearer than the advertising
Across three controlled trials, oral CBD did not produce a meaningful osteoarthritis pain advantage over placebo. That does not resolve every research question, but it is stronger evidence than testimonials or animal mechanisms. It also argues against delaying supported care in hopes that a retail CBD product will control joint disease.
Future studies can investigate other characterized formulations with transparent registration and adequate safety monitoring. Until positive, reproducible results appear, CBD should not be described as an evidence-based osteoarthritis supplement. The exact 2025 trial date and formulation should remain visible when it is cited, rather than being generalized to the entire market.
Placebo improvement is part of the result
In the knee trials, pain improved in both CBD and placebo groups. That pattern does not mean participants imagined their pain. Symptoms can fluctuate, background care continues, and expectations or study contact can influence reported experience. The placebo comparison estimates whether CBD adds a benefit beyond those shared influences. When the groups improve similarly, advertising only the CBD group’s baseline change is misleading.
Future cannabinoid studies should verify product content, disclose THC and other cannabinoids, monitor liver tests and interactions, and choose a primary outcome before enrollment. They should also report driving, sedation and withdrawal data. Until a specific formulation repeatedly beats placebo with acceptable safety, changing the delivery route or using “full spectrum” language remains a hypothesis rather than an evidence-based answer for osteoarthritis.
Sources & further reading
- Oral cannabidiol as add-on to paracetamol for knee osteoarthritis: randomized placebo-controlled trial ↗
- Cannabidiol in hand osteoarthritis and psoriatic arthritis: randomized placebo-controlled trial ↗
- CBD-rich Cannabis sativa oil in knee osteoarthritis: randomized placebo-controlled CANOA trial ↗
- FDA: What You Need to Know About Products Containing CBD ↗
This article provides educational information. Ask a qualified clinician or pharmacist about your symptoms, medical conditions, medicines and supplement interactions.