Cetylated fatty acids for knee pain: two trials do not validate every blend
Cetylated fatty-acid trials reported function and pain signals, but formulas, small samples, and commercial blends limit broad conclusions.
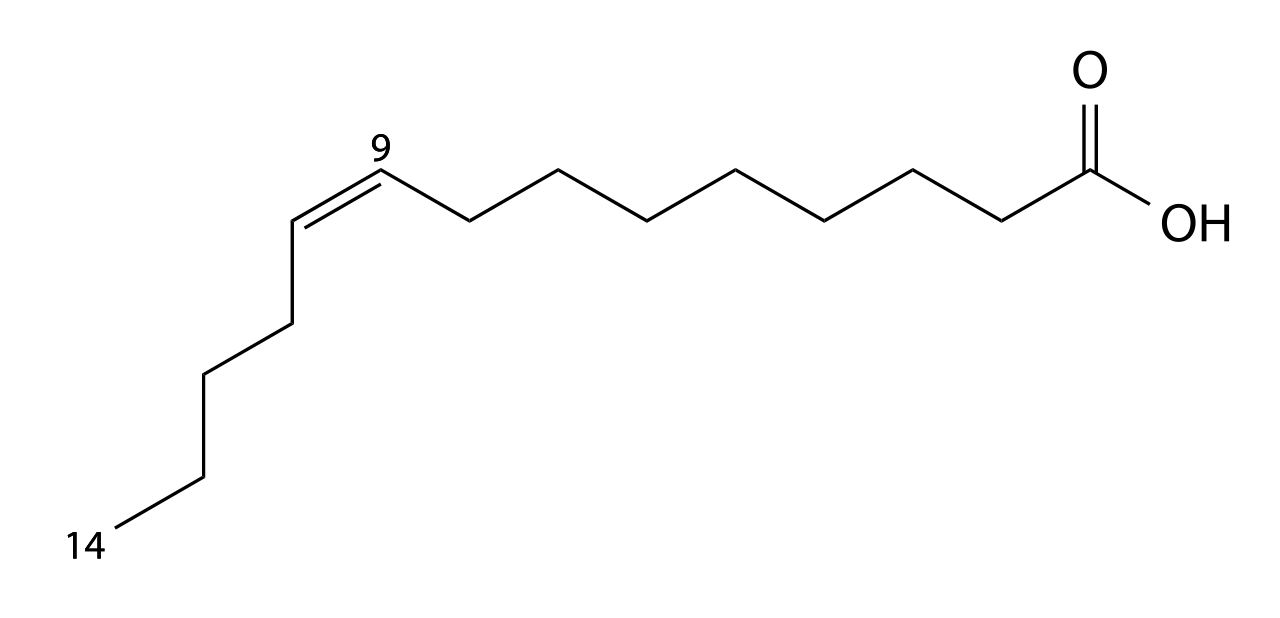
Early trials reported benefits with specific cetylated-fatty-acid products, but the evidence is small and formulation-specific.
A niche ingredient deserves a precise label check
Cetylated fatty acids can look refreshingly specific beside broad “joint complex” claims. The catch is that retail formulas may contain mixtures, while studies may identify one component or use a proprietary blend. The exact chemical profile is part of the evidence, not a technical footnote.
Two randomized trials offer a starting point for knee symptoms. They measured pain, range of motion, and function. Neither proves that these compounds rebuild cartilage, replace anti-inflammatory medicine, or work across every dose and blend.
An older trial reported better flexion and function
A 2002 randomized trial enrolled 64 people with chronic knee osteoarthritis. Participants consumed a cetylated-fatty-acid product or vegetable-oil placebo for 68 days. Knee flexion and a functional index improved more in the active group, while knee extension did not improve.
The findings are relevant because they included physical function rather than only a laboratory marker. Still, the sample was modest, follow-up was short, and the tested formulation matters. A result from one commercial mixture cannot be assigned to any bottle that uses a similar category name.
A later dose study was very small
A 2017 double-blind placebo-controlled trial randomized only 28 people with mild arthritic knee pain across three active formulations and a starch control. Some active groups reported greater pain and WOMAC improvements than control during 12 weeks, while one active group did not reach significance for pain.
With about six or seven people per group, a few individual responses can shift the result. Calling one concentration the “minimal effective dose” is therefore exploratory. The study is useful for generating a larger trial, not for guaranteeing a threshold on a retail label.
A blend name can hide the comparison you need
Cetyl myristoleate is often discussed as though it were the entire category. In practice, products may combine multiple cetylated fatty acids and other joint ingredients. That makes it hard to know which component matches a trial and which ingredient contributed to a response.
Ask for the amount of each active ingredient, not only the total blend weight. Confirm the serving size, number of daily servings, and whether the tested product was oral or topical. Ingredient transparency is especially important when several joint products are stacked.
Short trials leave safety and durability open
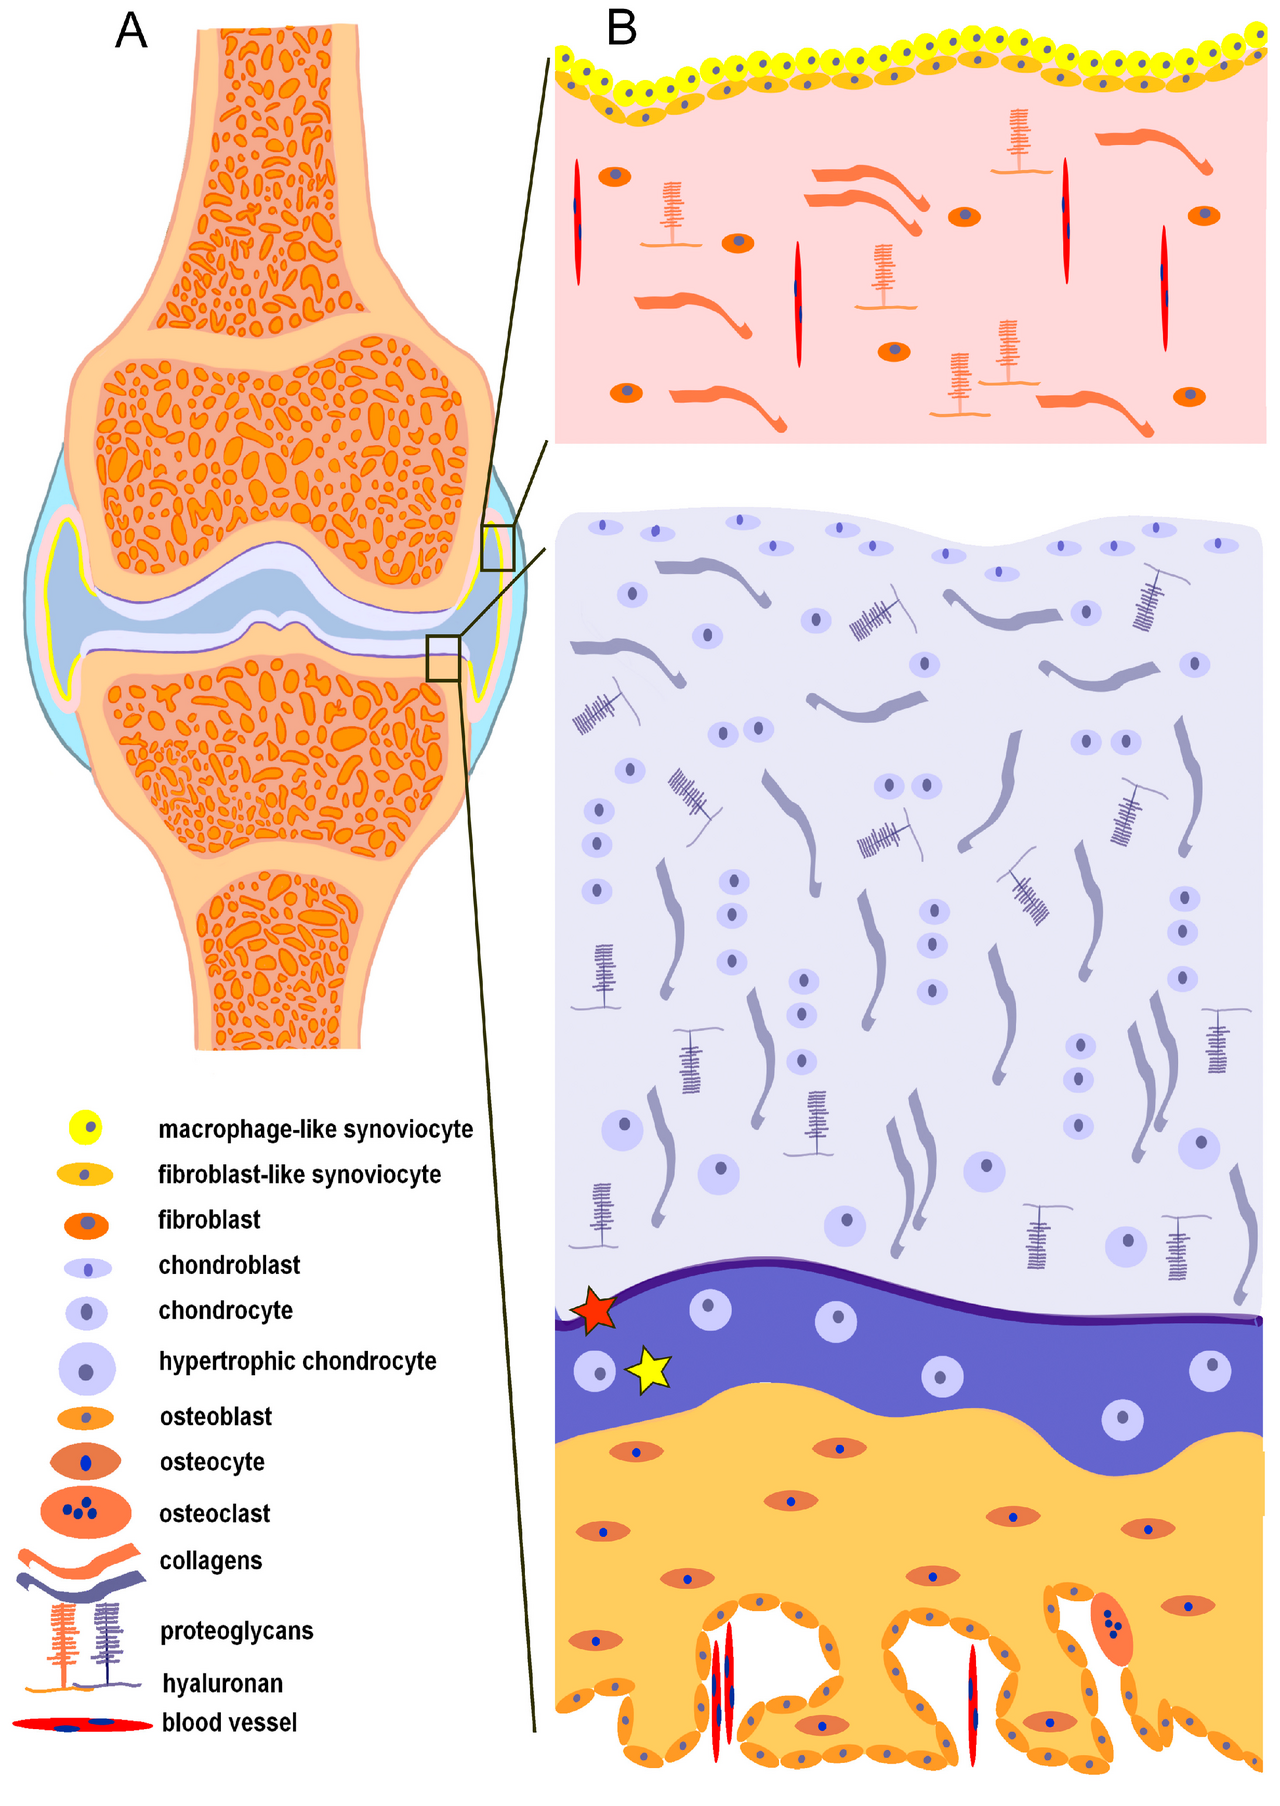
The available studies cannot establish years-long safety or sustained benefit. A person with food allergies, digestive sensitivity, surgery ahead, pregnancy, breastfeeding, or multiple medicines should ask a clinician or pharmacist before use. Quality testing also matters for an unfamiliar supplement category.
Knee pain after injury, a hot swollen joint, locking, fever, or rapid loss of function needs assessment. A supplement trial should never become a reason to postpone diagnosis or rehabilitation.
Turn the evidence into a modest test, not a promise
If a product closely matches a studied formulation, define a time-limited trial and meaningful goals with a health professional. Walking tolerance, stairs, sleep, and rescue medicine use are more informative than waiting for a dramatic sensation. Stop if adverse effects occur.
The current evidence is neither empty nor decisive. Two small trials suggest that selected cetylated-fatty-acid preparations may affect pain or function. The responsible conclusion stops there: a formula-specific possibility that needs larger independent replication.
Look for the details that small studies cannot supply
A stronger future trial would enroll enough people to detect a clinically meaningful difference, register one primary outcome in advance, use a convincing placebo, and report adherence, rescue medicine, and adverse events. It would also identify every active fatty acid and follow participants long enough to test durability.
Until that evidence exists, product transparency is the shopper’s best filter. Avoid formulas that hide amounts in a proprietary total or imply joint lubrication from a mechanism alone. Clear chemistry does not guarantee clear clinical value, but an unclear label makes a research match impossible from the start.
Independent replication would also help separate a reproducible ingredient effect from results tied to one commercial preparation.